When a clinician refers a patient to a specialist, scheduling the appointment is only one part of the coordination process. The referral has to reach the receiving practice, contain enough information to be reviewed, move through scheduling and the consultation, and result in information returning to the referring care team.
That closed-loop specialty-referral process provides a useful model for a broader operational problem. A referral can exist in a clinical record while the work surrounding it still depends on people tracking status, exceptions, follow-up, and outstanding actions across the systems they use.
Referral tracking makes the work accountable: every referral has a responsible party, a visible current state, and a defined path to completion. The harder part is knowing what completion requires and identifying the work that remains unresolved before the referral gets there.
What the Referral Coordination Workflow Involves
The ambulatory specialist-referral process can look like the clinician sends to the specialist, consultation, information and then back to the referring team, is the referral workflow with the most documented operational guidance. What follows draws on that model. Where the operational argument extends to other referral contexts, this article says so explicitly rather than assuming the evidence travels with it.
Referral request and review. The referral moves from the referring clinician to the receiving practice, carrying the information needed to determine whether and how it can be acted on: the reason for the referral, relevant clinical information, insurance and authorization requirements, and urgency. The first coordination question is whether the referral has arrived with enough to move forward. If it has not, the coordination process has already encountered its first branching point. The referral may need to go back before it can proceed.
The operational question at this stage: has the referral reached the point where someone can act on it?
Scheduling and access. The expected path from here is appointment scheduling, then consultation. But a referral can also remain unscheduled, be cancelled, result in a no-show, or require rescheduling. Those are not variations a tracking process can treat as the same state. Each one leaves different work unresolved and requires a different next action. Where prior authorization applies before scheduling, that workflow runs in parallel. The authorization process is covered in detail in prior authorization tracking; the referral coordination workflow picks up once authorization is confirmed or verified as not required.
Some practices also track appointment confirmation as part of their scheduling process. The ambulatory closed-loop frameworks reviewed did not establish this as a standard coordination stage. It is treated here as an optional operational field reflecting a local workflow choice, not a core referral step.
Consultation and return communication. After the appointment occurs, the referral coordination process does not necessarily end. The specialist's findings or report return to the referring clinician. In the ambulatory specialty-referral model, this communication back to the referring team is part of what constitutes a closed referral loop, not simply that a consultation occurred.
CMS quality measure CMS 50 tracks whether referring providers receive a specialist report within a defined timeframe. IHI's closed-loop referral framework and ACP professional care-coordination guidance both treat return communication as part of the complete referral process. That is professional guidance and a specific quality measure, not a universal regulatory requirement. Requirements can vary by context.
Closing the loop. Two things called "closure" need to be kept distinct here.
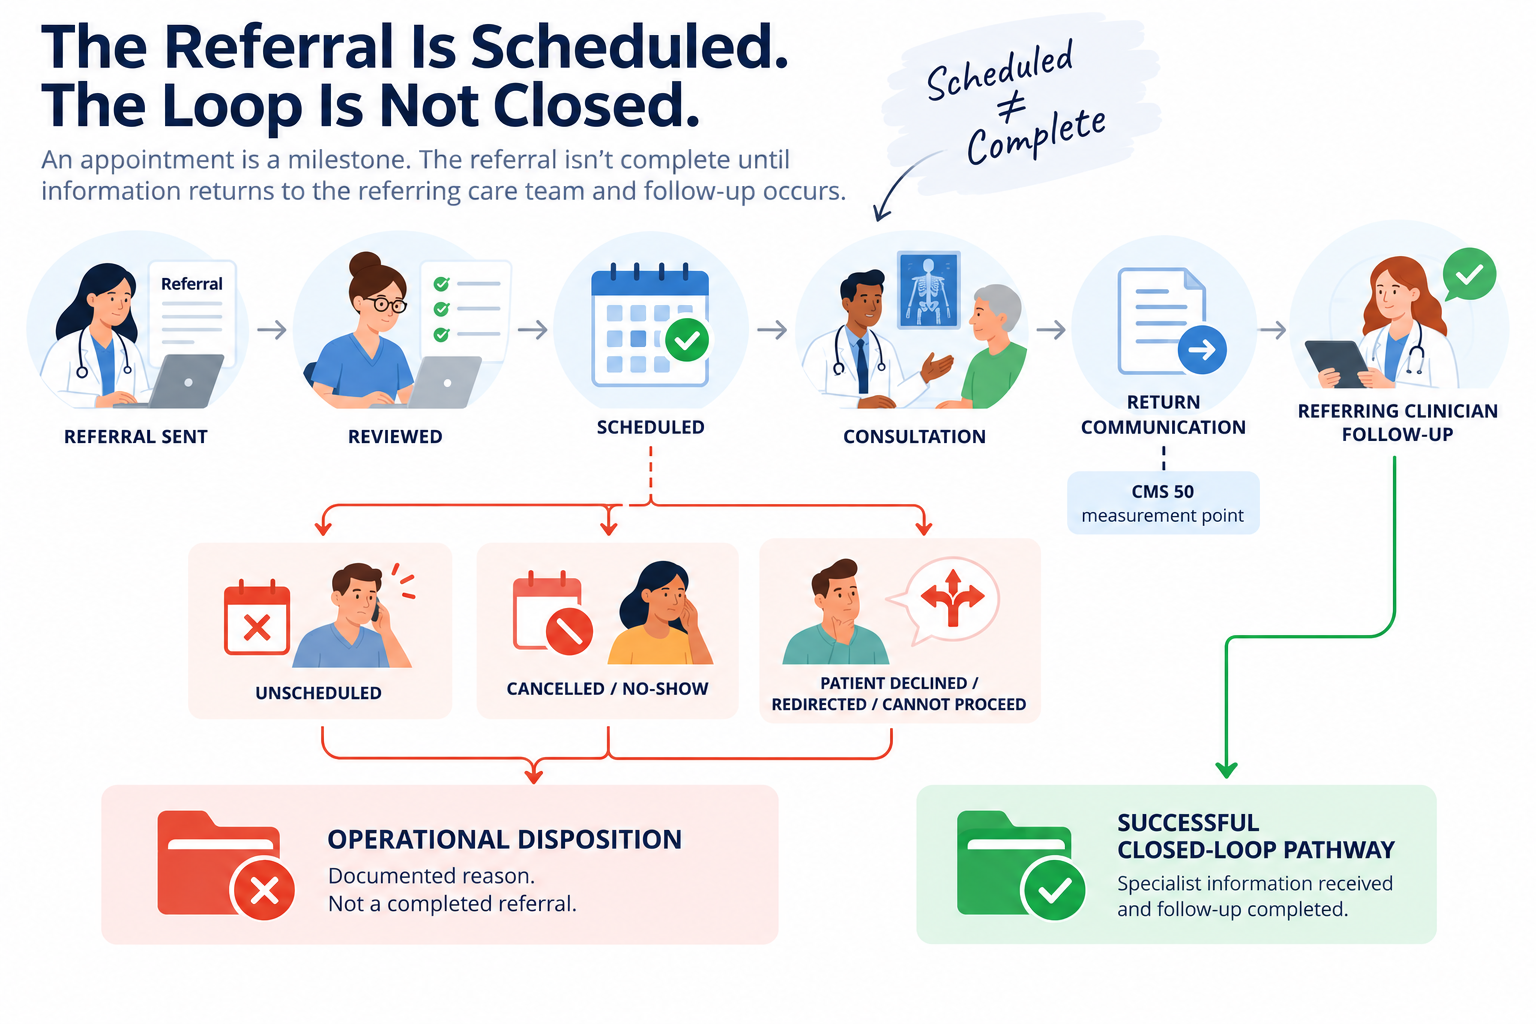
A closed referral loop in the ambulatory specialist model is a broader concept than any single measurement endpoint. IHI's nine-step closed-loop referral process continues after consultation and specialist communication through the referring clinician acknowledging receipt of the specialist's plan and communicating the resulting plan to the patient and family. CMS 50 uses a narrower, specific measurement point: the referring clinician receives the specialist's report. Both treat return communication as necessary; they define the process's extent differently.
"Successful loop completion" in this article means the expected return communication and follow-up defined by the referral guidance and the organization's process, not a single universal endpoint. CMS 50's report-receipt criterion is one concrete, measurable marker within that broader pathway.
An operationally closed referral record means the organization has completed or documented the actions required under its process. Not every referral reaches the successful closed-loop endpoint. A patient may decline the referral, an appointment may never occur, or another condition may prevent the expected pathway from continuing. Those outcomes are not equivalent to successful loop closure. CMS 50 is explicit that patient refusal does not satisfy the measure's numerator, which requires the specialist's report. For operational tracking purposes, organizations can distinguish those cases through documented disposition states so they do not remain indistinguishable from active work still in progress. AAFP guidance supports documenting patient refusals; the disposition categories themselves are local operational design, not a prescribed national taxonomy.
A referral that ends at consultation-with-return-communication closes differently than one that ends at patient-declined or referral-redirected. Both need a closure basis: a specific event or documented outcome that ends the coordination process for that case. What the tracking process cannot do is treat "scheduled" as a default stand-in for "finished," because scheduled is neither closure type.
Where Referral Coordination Breaks Down
Referral coordination can break down even when the underlying information has been recorded. The failures below concern what happens between stages: unclear responsibility, unresolved exceptions, missing return communication, and limited visibility into active work.
The ownership gap. A referral can arrive, be logged, and have no named person responsible for the next action. The record establishes that the referral exists; it does not establish who schedules it, who follows up if the patient does not call back, or who carries it to the coordination endpoint. In the ambulatory referral model, defined responsibilities are part of what makes the process function. When responsibility for the next step is unclear, the referral has been received but not managed.
The scheduling gap. A scheduled appointment is one state. An appointment that was never scheduled, cancelled, missed, or needs rescheduling after a no-show represents a different coordination condition and a different unresolved action. A tracking process that treats all of those as variants of "scheduled" has lost the information it needs to know what happens next.
The exception gap. The expected referral path is straightforward on paper. The operational work appears when the expected next event does not happen: a referral remains unscheduled past the point where someone should have acted on it; a patient does not attend and no follow-up is logged; a specialist's response has not returned by the time the referring clinician needs it; a referral has been in one status longer than makes operational sense. A tracking system that records states but does not bring aging and exception conditions into view has the data without the coordination logic. What counts as "too long" depends on urgency designation and the organization's service expectations. The threshold is local, not universal. The need to identify it is not.
The return-communication gap. In the ambulatory specialist-referral model, the coordination process extends beyond the consultation. A 2023 workflow analysis of cross-institutional specialty referrals identified 25 barriers specifically within the closing and information-gathering portion of the workflow, most involving either the consultant team sending visit notes or the referring team trying to locate them. A consultation can occur while the referring team is still waiting for the specialist's report. If the tracking process treats the appointment as the endpoint, the remaining coordination work loses its owner.
The volume visibility gap. When referrals are tracked across individual spreadsheets and email threads, producing a current view of active referrals, status, aging, and exception conditions requires bringing those records together. The picture is outdated before it is finished. A coordinator or manager cannot see what is active, overdue, or stalled without assembling the information first, and the assembly is not the coordination work; it is overhead that delays it.
The history gap. When the operational record of a referral is distributed across phone notes, email, and spreadsheet fields, the next person who needs to act on it may not be able to reconstruct what has already happened. The referral has a record; the process that produced it may not.
What a Referral Tracking System Needs to Include
The field list below is divided into two explicit categories. The first covers information that the referral process itself requires, grounded in the ambulatory specialist-referral model and healthcare coordination guidance. The second covers information the operations team may need to manage the work. Those are operationally useful fields, not claimed as healthcare standards.
Information the referral process requires
These fields reflect what the coordination process needs to function, drawn from the evidence-backed ambulatory referral model:
- Patient or referral identifier
- Referring clinician and practice
- Receiving specialist and practice
- Reason for referral
- Urgency or priority designation
- Relevant referral information provided at intake
- Appointment status: scheduled / unscheduled / cancelled / no-show / rescheduled
- Return communication status: whether the expected specialist response has been sent or received; this field tracks the occurrence of the communication, not its clinical content. Return communication is part of the healthcare-grounded ambulatory referral process. Which role records, monitors, or acts on this event depends on the organization's workflow.
- Return communication date
Information the operations team may need to manage the work
These are operational design fields. They are not a standardized healthcare data model. An organization may use some, all, or different fields depending on how its coordination workflow is structured:
- Internal owner: the person responsible for the next action on this referral
- Current operational status: the internal tracking state. The reviewed sources did not establish a universal status vocabulary; IHI gives process stages and implemented systems translate those into their own statuses. The following list is illustrative, not prescribed: Received / In Review / Pending Authorization / Scheduled / Awaiting Return Communication / Complete / Exception / Terminal Disposition. Organizations should translate meaningful workflow stages and exception conditions into their own operational statuses.
- Next action and due date
- Aging indicator: how long the referral has been in its current state
- Exception state: whether the referral has reached a condition that requires intervention
- Contact log: structured entries for each patient contact, with date, method, outcome, and next action logged as separate entries, not accumulated in a running notes field
- Authorization required: yes/no, and authorization status if ye
- Escalation flag
- Closure date
- Closure basis: the specific event or documented outcome that ends the coordination process for this referral. Two categories apply: successful pathway completion and documented noncompleted disposition. Noncompleted dispositions are not recorded as successful pathway completion. The specific disposition labels are local operational design.
Appointment confirmation note: the ambulatory closed-loop frameworks reviewed did not establish patient appointment confirmation as a standard coordination stage. It is an optional operational field for organizations whose workflow includes it, not a core referral coordination step.
Receipt Is Not Coordination
The three-level framework below is this article's operational framework, not a healthcare-standard set of referral statuses. It is a way of naming the coordination problem precisely.
A referral that is received and a referral that is managed are not the same thing.
Received means the referral exists and is available for action. Managed means responsibility and next action are established, and the referral's current condition is visible. Closed means the organization has reached its defined coordination endpoint and has no unresolved action remaining under that process.
Those are three different states. The gaps between them are where accountability disappears.
From received to managed: a record without an owner is not a managed case. A referral can be logged in a spreadsheet, an EHR field, or an inbox without establishing who schedules it, who follows up when the expected next event does not happen, or who carries it to the coordination endpoint. Making a referral a managed item requires explicit ownership: a named person, a visible workload, and accountability for what happens between receipt and closure.
From managed to closed: ownership over a referral's next action is not the same as coordination logic over the referral's full lifecycle. The dates and statuses needed to identify which referrals are active, overdue, or in an exception state may all be present in a record without registering as anything. A referral that has been unscheduled past a reasonable threshold, or whose return communication has not arrived, needs to appear in the team's follow-up queue rather than wait for someone to go looking for it. Data plus ownership does not automatically produce coordination; the system needs to do something with the aging information, not merely hold it.
The closure problem: the ambulatory model distinguishes two things worth keeping separate throughout the tracking process. A closed referral loop is the successful pathway through consultation, return communication, and the follow-up that guidance describes. IHI's model continues through the referring clinician acknowledging the specialist's plan and communicating it to the patient; CMS 50 provides one specific measurement marker within that pathway: receipt of the specialist's report. An operationally closed referral record is the organization's documented endpoint, including exceptions where the successful pathway was not reached. A patient who declines, a referral that is redirected, an authorization that fails: none of those reach successful pathway completion, but all of them need a documented disposition before the coordination process can end. A tracking system that only accounts for the successful pathway has no mechanism for closing those cases. The disposition categories are local operational design; the distinction between successful completion and noncompleted disposition is healthcare-grounded.
A referral tracking system needs to carry the workflow from receipt through managed accountability to its defined endpoint, with ownership, aging, and next actions visible while the referral remains active.
An EHR can support referral ordering, scheduling, documentation, status tracking, and return communication, particularly when referring and specialist teams share an integrated environment. Coordination becomes harder to keep visible in a single system when a referral crosses organizational or technology boundaries. A 2023 workflow study of cross-institutional specialty referrals found that when referring and specialist teams do not share an EHR, visit notes can move through fax, email, phone, external EHRs, health information exchanges, or the patient directly. If the referring team does not receive them, staff may have to search across multiple channels to locate them. The researchers identified 25 barriers specifically in the closing and information-gathering phase. A companion study found limited adoption of health information exchange technology and continued fax use among the barriers to closing cross-institutional referral loops.
The operational problem this article addresses is not that EHRs fail at referral management. It is that when coordination work extends across organizational and system boundaries, or depends on people managing status, exceptions, and follow-up outside a shared clinical environment, the work can lose visibility, ownership, and the aging logic needed to bring what still needs attention into view.

Kintone can be configured around this operational layer without replacing the clinical systems involved in the referral. Each referral can be maintained as a record with the fields the team needs to manage its work. Process Management can assign responsibility at each workflow stage and move the record through the organization's configured statuses and conditional workflow paths, so the person responsible for the next action is visible alongside the referral's current state. Date fields, filtered views, and reminder notifications can identify referrals that need follow-up before someone has to go looking for them. Related records can connect supporting operational information maintained across Kintone apps. The return-communication status field tracks whether the expected communication has occurred, without requiring Kintone to store the specialist's report. That stays in the clinical system where it belongs.
That makes Kintone useful when the coordination problem is visibility: knowing which referrals are active, who owns the next action, which cases have stalled or reached an exception condition, and which have reached the organization's defined endpoint. Kintone also provides REST APIs, outgoing webhooks, and other integration mechanisms that can support data exchange and workflow connections with external systems. Whether Kintone can connect to a specific EHR, and what information should move between the systems, depends on that system's available integration methods and the implementation.
Managing the Full Loop with Kintone
Scheduling tells you an appointment exists. It does not tell you whether the consultation occurred, whether a cancelled appointment requires another action, whether the specialist's report has come back, or whether anyone still has work to do.
For ambulatory specialty referrals, closed-loop guidance provides a defined path: referral, consultation, and return communication back to the referring team. The operational lesson extends further. Whatever referral process an organization uses, the people managing it need to know what state the referral is in, what remains unresolved, and who is responsible for what happens next.
Receipt, ownership, and closure are three different things. A referral system that records receipt without establishing ownership has solved a filing problem, not a coordination problem. A system that establishes ownership without carrying through to the coordination endpoint has solved part of the problem. The full workflow requires all three.
For ambulatory specialty referrals, the successful pathway extends beyond scheduling and consultation through return communication and follow-up. CMS 50 provides one defined measurement point within that pathway: the referring clinician receives the specialist's report. Where a referral does not reach the expected pathway because the patient declined, authorization failed, or the referral was redirected, the operational record needs a documented disposition that distinguishes the case from work still in progress. Until successful completion or a documented disposition is reached, the referral coordination process is still in motion.
The operational layer alongside your EHR can look like the work that is not adequately visible or managed in your current clinical systems, particularly when referrals cross organizational and system boundaries, which is the focus of Managing the Work Your EHR Doesn't and looks across the workflows coordination teams handle daily.
See how Kintone could be configured around referral ownership, status, follow-up, exceptions, and closure without replacing the clinical systems your team relies on by requesting a demo to ensure you get the guidance you need.


About the Author